
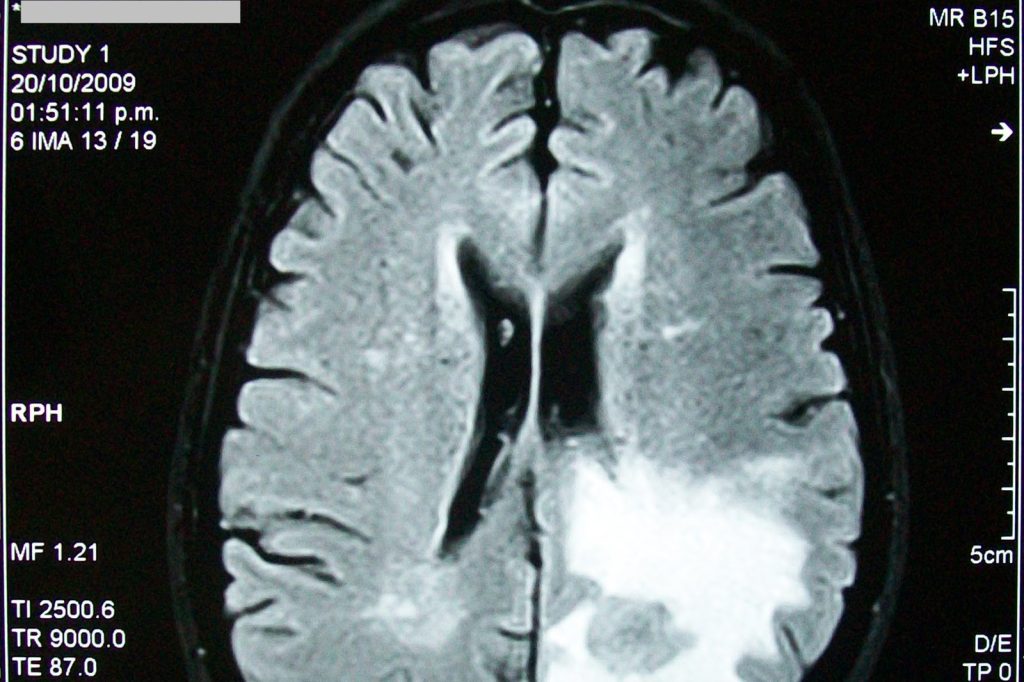
Median overall survival: 42.5 months with GammaTile, 17.6 months with the current standard. That is the figure that matters in a randomized trial of patients whose brain metastases needed surgery.
The trial is called ROADS (NCT04365374), and it is the first randomized phase 3 study to put GammaTile, a cesium-131 collagen tile-based radiation therapy, head to head with stereotactic radiation therapy (SRT) delivered after surgery. Jeffrey Weinberg, a neurosurgery professor at MD Anderson Cancer Center, and Thomas Beckham, a radiation oncologist there, co-led it. GT Medical Technologies, which makes the device, announced on September 29, 2026 that the Journal of Clinical Oncology had published the results as a Rapid Communication, a designation the journal’s editors grant at their discretion. The data were first presented at the 2026 ASCO Annual Meeting.
The numbers
One year after surgery, the tumor had come back at the surgical site in 1.3% of patients treated with the tiles. In the SRT group the rate was 15.4%. Put the other way, GT Medical reported local tumor control of 98.7% against 84.6%, a cut of more than 90% in the risk of recurrence at the surgical bed (HR 0.07, p=0.012). The combined risk of recurrence or death fell by more than 50% (HR 0.48, p=0.002).
The survival gap carried a hazard ratio of 0.59 and p=0.032.
“From a patient standpoint, we’re showing that there’s almost four times the length of local control and an increase in overall survival,” Weinberg said. “It’s not just a little difference. It’s a massive difference.”
How the tiles work
Each tile is roughly the size of a stamp. Seeds loaded with cesium-131 sit in a collagen matrix, and the surgeon lines the empty cavity with them before closing. The seeds give off low-dose radiation for several weeks, and because the dose drops off quickly with distance, little healthy brain tissue is exposed. The FDA has cleared the device.
Timing is the practical difference. Without any radiation, tumors return in the cavity 50-60% of the time, which is why post-operative SRT is standard, ideally within four weeks of surgery. Most patients in the tile arm finished cranial radiation in a single day. Those waiting on SRT had a median of 32 days.
That speed matters to people who still have a primary cancer to fight. Beckham called the results “dramatically better than the current alternatives.” Getting patients past the diagnosis faster, he said, seems to help more than the surgical outcome alone, to a degree the team had not expected.
Safety and the authors’ call
Serious treatment-related side effects did not differ between the two groups. Radiation necrosis, a late risk of brain radiation, occurred at nearly identical rates.
The authors concluded that, for newly diagnosed brain metastases, GammaTile belongs among the accepted standard options. They pointed to the multicenter randomized design, follow-up longer than in the studies that made post-operative SRT the standard, and a win on both co-primary endpoints. The researchers hope the findings speed up inclusion in treatment guidelines, and they plan to test the approach in other tumor types.
Sources
- Radioactive collagen tiles double survival for brain metastasis patients (MD Anderson)
- Publication of ROADS Phase 3 Clinical Trial Data in JCO (GT Medical Technologies)




